ℹ️ This is the case information for the doctor.
Name
Amanda Davies
Age
32 years
Address
73 Drake Avenue
Social history
Marital Status: Married to Mark Davies, age 44.
Smoking: Does not smoke.
Alcohol: Does not drink.
Past history
Investigation results
Medication
Booking note
Requests appointment for conception advice.
ℹ️ This is the information for the person role playing the patient.
Name
Amanda Davies
Age
32 years
Address
73 Drake Avenue
Social history
Marital Status: Married to Mark Davies, age 44.
Smoking: Does not smoke.
Alcohol: Does not drink.
Past history
Medication
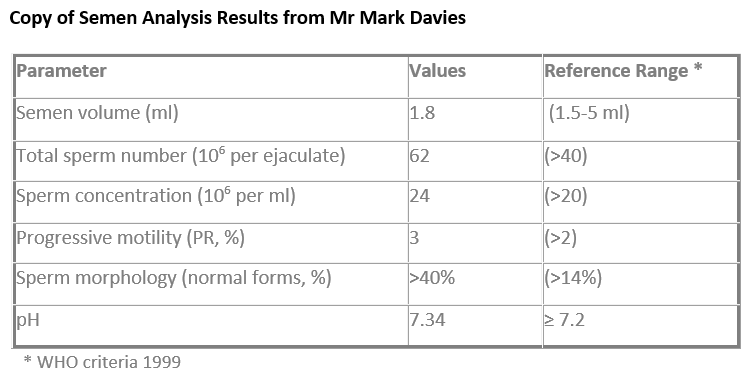
Sorry to trouble you doctor but I wondered if you might be able to refer me to an infertility specialist… I also wondered if you can tell me the result of Mark’s semen test he had last week, you should have them back by now
Living situation: Recently moved into a new house with Mark. Wedding in 3 months (planning ceremony now).
Employment: Works at Sainsbury's as a checkout assistant.
Marital Status: Married to Mark Davies, age 44, estate agent.
Medication taken over the counter: Prenatal supplement: Pregnacare tablets (self-purchased, not prescribed).
General health: You are otherwise well, taking Pregnacare, and not on any other medication.
Gynae history
ℹ️ To mark data gathering & diagnosis select from the descriptors below.
Positive descriptors
Negative descriptors
Data gathering was systematic and targeted ensuring patient safety.
Data gathering was incomplete, lacking structure and focus.
Makes effective use of existing information and considers the wider context.
Fails to use the information provided or understand the wider context.
The presence or absence of relevant red flags was established.
Fails to assess key information necessary to determine risk.
Information gathered placed the problem in its psychosocial context.
The social and psychological impact of the problem was not adequately determined.
Relevant information was collected to place the undifferentiated problem in context and an appropriate differential diagnosis generated.
Inadequate information was collected to determine the likely cause of symptoms.
Revises hypotheses as necessary in light of additional information.
Rigid consulting with new information not adequately considered and integrated into the working diagnosis.
ℹ️ To mark clinical management & medical complexity select from the descriptors below.
Positive descriptors
Negative descriptors
Offers management options that are safe and appropriate:
Fails to provide appropriate and/or safe management choices:
Continuity of care is prioritised:
Ongoing care is uncoordinated:
Empowers self-care and independence:
Management fails to foster self-care and patient involvement:
Prescribes safely considering local and national guidance:
Unsafe prescribing ignoring best practice:
Practises holistically, promoting health, and safeguarding:
Fails to safeguard patient welfare:
Does not break Mark’s confidentiality:
Breaks Mark’s confidentiality:
ℹ️ To mark relating to others select from the descriptors below.
Positive descriptors
Negative descriptors
Explores the patient’s agenda, health beliefs and preferences:
Fails to recognise the patient’s agenda and impact of the problem:
Recognises what matters to the patient and works collaboratively to enhance patient care:
Fails to work with the patient to plan care:
Demonstrates flexibility of communication adapting to the patient and scenario:
Consults rigidly, providing generic explanations and management plans:
Respectfully challenges unhelpful health beliefs or behaviours:
(80% of women aged under 40 years conceive within 1 year, 90% within 2 years)
Fails to maintain a productive therapeutic relationship:
Checks the patient’s understanding of the consultation including any agreed plans:
Does not seek to confirm understanding:
Adapts thinking to overcome challenges, creating practical and effective solutions:
Fails to adjust thinking when faced with obstacles, leading to ineffective or impractical solutions:
ℹ️ Insights from the examiner
Case at a glance
Amanda is seeking advice because she and Mark have been trying to conceive and are worried that pregnancy has not happened as quickly as expected. She may be hoping for early investigations, referral or access to Mark’s results.
The consultation should provide supportive, structured fertility advice, clarify whether there are risk factors requiring earlier assessment, explain why routine investigation is usually deferred until 12 months of trying where there are no red flags, and agree a clear follow-up plan.
GP trainee performance focus
A strong GP trainee should demonstrate the ability to:
What this case is testing
Patient priorities and concerns
Amanda may want:
Central challenge
The central challenge is to balance reassurance with validation.
Amanda may not need immediate investigation if she has regular cycles, normal sexual frequency and no red flags, but she still needs to feel heard and supported. The trainee must avoid:
Must-not-miss issue or diagnosis
The must-not-miss issue is identifying risk factors that would justify earlier fertility assessment, such as:
In the information provided, Amanda has no urgent red flags for early female investigation per NICE CG156.
Red flags or high-risk features
Features to ask about include:
Common GP trainee pitfalls
What good looks like
A strong consultation is supportive, structured and realistic. The trainee acknowledges Amanda’s distress, checks for red flags, explains why waiting until 12 months is appropriate if no risks are present, and agrees what will happen next.
“From what you’ve told me, there don’t seem to be obvious reasons for delay. National guidance usually recommends arranging further tests after 12 months of trying, but I’ll explain exactly what we would do then and what would make us review things sooner.”
Learner checkpoint
Have I reassured Amanda with a clear plan, rather than simply telling her to keep trying?
Start with an open question
Start with an open-ended question to encourage Amanda to share her story.
“I can see this is really important to you. How have things been for you and Mark recently?”
Then clarify her agenda:
“What are you hoping we can achieve together today?”
This helps identify whether she wants reassurance, tests, referral, advice about timing, information about Mark’s results, or emotional support.
Time-efficient data gathering
Aim to complete data gathering by around 6–7 minutes, leaving adequate time for management.
Use focused questions to clarify:
Avoid questions that do not directly relate to the case.
High-yield questions
Trying to conceive
Menstrual history
Medical and surgical history
Partner factors
Previous investigations
“Have either of you had any investigations before, for example blood tests or hormone checks?”
Clarify what has been done to avoid repetition and respond proportionately.
Functional, psychosocial or contextual assessment
Explore the emotional and relationship impact.
“You mentioned that this has been difficult for you and Mark. Can you tell me more about how you’re both coping?”
Ask about:
Explore ideas, concerns and expectations
Amanda may expect early referral or investigations. Explore this gently.
“Would it help to know more about what to expect and when we would refer if it was needed?”
If she appears worried that referral is not being offered immediately:
“That’s a very common reaction when things aren’t happening as quickly as hoped, but you’re certainly not alone. Can you tell me more about what you’ve found most difficult?”
Recognise and respond to cues
Look for cues suggesting:
Respond with validation:
“Trying for a baby can be a very emotional process, especially when things are taking longer than you expected.”
Useful consultation phrases
“Most couples will conceive within 12 months of trying. If it hasn’t happened by then, we can arrange further tests for both you and Mark.”
“Everything you’ve told me so far is reassuring, but I don’t want to dismiss how stressful this feels.”
“If cycles change, symptoms develop or we identify any new risk factors, we can review things earlier.”
“I can’t give Mark’s results to you without his explicit consent, but we can arrange a joint appointment or he can contact the practice directly.”
Consultation flow and signposting
Summarising and checking understanding
Summarise as you go to stay aligned with Amanda’s agenda.
“Your periods sound regular, you and Mark are having sex regularly, and you’re both generally healthy, which is reassuring. You’re understandably worried because it’s taking longer than you expected, and you’d like to know whether tests or referral are needed now.”
Check:
Data gathering self-check
Before moving to management, the trainee should know:
Assessment domain mapping
Data gathering
Clinical management
Relating to others
Prioritised differential diagnosis or clinical reasoning
In a woman with regular cycles, normal sexual frequency and no red flags, differentials include:
Amanda has no urgent red flags for early female investigation per NICE CG156 based on the information provided.
Clinical reasoning script
“From what you’ve told me, there aren’t obvious warning signs that we need to investigate straight away. Fertility specialists usually work with couples who have been trying for a year or more, because the vast majority of couples will get pregnant within a year of trying. If it hasn’t happened by then, we can arrange tests for both of you.”
Red flags and risk assessment
Review earlier or consider earlier assessment if:
Decision points
Key decisions include:
Management priority
The management priority is to provide Amanda with a clear, reassuring and actionable plan:
Management options
1. Continue regular sexual intercourse
Advise regular intercourse every 2–3 days, which maximises natural conception chances.
2. Prenatal supplements and healthy lifestyle
Discuss:
3. Immunisations
Ensure both partners are up to date with relevant immunisations, including checking rubella vaccination status.
4. Stress and psychological support
Offer support for stress, relationship strain or emotional impact.
Options may include:
5. Mark’s health and results
Offer review of Mark’s health and lifestyle, including support for quitting smoking if applicable.
If Amanda expects Mark’s result, explain:
“I understand why you’d want to know, but I can’t provide Mark’s results without his explicit consent. He can contact the practice directly, or we can arrange a joint appointment if he agrees.”
6. Follow-up plan
Arrange review at 12 months of trying, or earlier if:
7. Future investigations and referral
Explain what may be considered if pregnancy has not occurred after 12 months, including:
Make clear that these are not automatically required immediately if there are no risk factors.
8. Written resources
Offer reliable fertility information, including:
Personalised plan
For Amanda, a personalised plan might include:
Example phrase:
“I know it must feel frustrating, but the good news is that everything you’ve mentioned is reassuring and in line with what we’d hope for at this stage. Can I suggest we make a follow-up appointment for five months’ time, to reach the 12 months, and earlier if anything changes?”
Shared decision-making
Involve Amanda in the plan.
Ask:
“Would that work for you, or is there something else you’d like to discuss today?”
Check whether she wants:
Safety-netting
Advise Amanda to seek earlier review if:
Ethical, legal and safeguarding considerations
If Amanda asks for Mark’s results, explain sensitively that his results cannot be shared without his explicit consent.
This is supported by GMC Confidentiality.
Offer alternatives:
Documentation points
Document:
Common unsafe management plans
Avoid:
Follow-up and coordination with other professionals
Arrange follow-up at 12 months of trying, or earlier if new concerns arise.
Consider coordination with:
Learner checkpoint
Have I given Amanda a clear plan for what happens now, what happens at 12 months, and what would trigger earlier review?
Relevant guidance areas
NICE guidance
GMC, DVLA or safeguarding guidance
Patient information websites
Key principles to remember
Transferable learning for future cases
In fertility consultations:
Supervisor or examiner lens
A supervisor or examiner is likely to look for:
Final learner takeaway
In early fertility concerns, combine empathy with structure: check for red flags, support the couple, avoid premature tests, and give a clear plan for review.


